A patient does not need an ICU because of a diagnosis label alone. The deciding issue is whether the illness is causing, or is close to causing, organ failure that requires life support, continuous monitoring or rapid intervention; you will learn which warning signs demand emergency transport and how clinicians choose the right level of care.
Key takeaways
- Call emergency services for failing breathing, circulation, consciousness, or multiple organs.
- ICU care provides continuous monitoring and organ support unavailable on a standard ward.
- Ask which test results, treatments, and risks prompted ICU specialist involvement.
- Bring medicines, allergies, medical records, and the patient’s decision-maker details.
Which warning signs mean the patient needs emergency assessment now?
Treat a patient as needing emergency assessment when critical illness definition signs appear: an organ is failing or may fail without rapid treatment.
Severe breathlessness, oxygen saturation below target despite prescribed oxygen, blue or gray lips, new confusion and inability to stay awake, fainting, or inability to speak normally because of breathlessness require emergency medical services, not a clinic visit or private driving.
During rehabilitation, stop exercise immediately for new chest pressure, syncope or near-syncope, severe breathlessness out of proportion to the workload, cyanosis, sudden marked loss of exercise tolerance, or rapidly worsening weakness. Do not simply reduce the workload. These signs can indicate a heart attack, dangerous arrhythmia, pulmonary embolism, shock, or respiratory failure.
| Warning sign | Why it matters | Immediate action |
|---|---|---|
| Persistent low oxygen | Oxygenation may be failing | Call emergency services; report the reading and prescribed target |
| New confusion or inability to stay awake | The brain may not be receiving enough oxygen or blood flow | Keep the patient supervised and request urgent transport |
| Fainting, seizure, or very low blood-pressure symptoms | Shock or a serious rhythm problem is possible | Lay the patient safely, avoid food or drink, and call emergency services |
| Sudden severe weakness or rapidly falling urine output | A major infection, kidney injury, or other organ failure may be developing | Seek emergency assessment; do not wait for a routine appointment |
What separates ICU care from ward, observation or home monitoring?
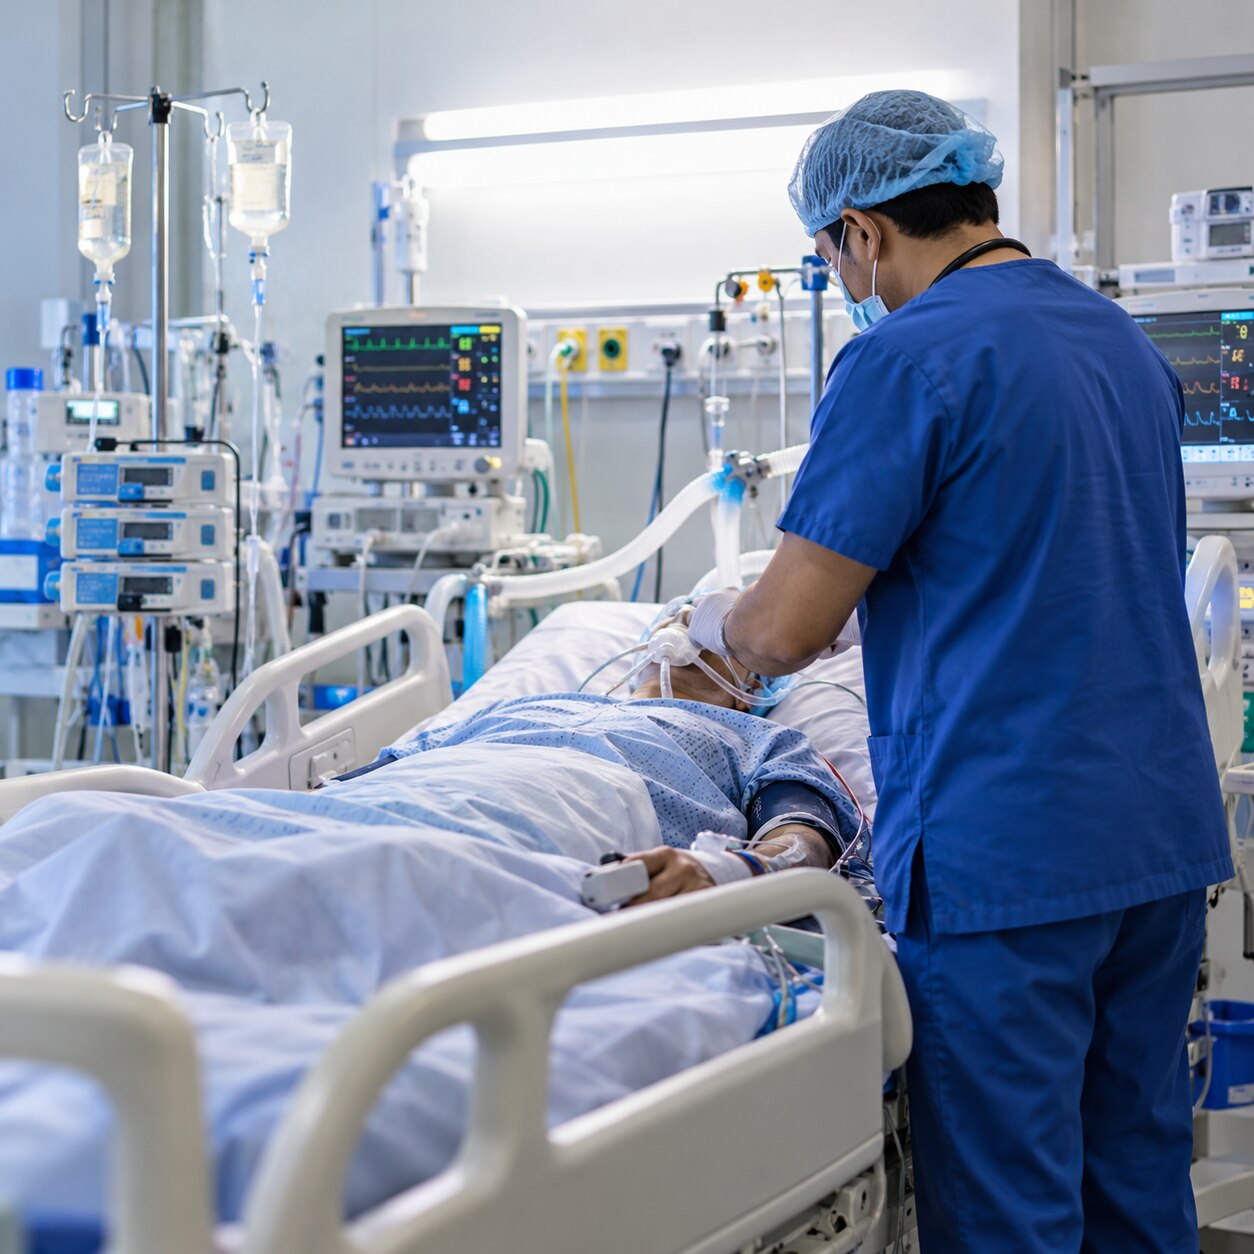
The key question is whether the patient needs organ support or observation that a regular ward cannot safely provide. ICU admission criteria include actual or impending failure of breathing, circulation, brain function or other organs, not a diagnosis label alone; clinicians also consider reversibility, treatment goals, baseline function and available monitoring.
| Setting | What it means | When it applies |
|---|---|---|
| Home monitoring | Stable illness with a clear safety plan | Symptoms are mild, vital signs are stable, and the patient can take medicines and return promptly if worse |
| Emergency-department observation | Short, repeated assessment | The diagnosis or response to treatment is uncertain, but there is no current need for organ support |
| General ward | Routine inpatient treatment | The patient needs hospital medicines, oxygen or tests without minute-to-minute intervention |
| Step-down unit | Closer observation than a ward | The patient is improving after critical illness or needs frequent checks, but not full ICU support |
| ICU | Continuous monitoring and life support | The patient has unstable organ function, shock, dangerous arrhythmias or rapidly worsening breathing |
Use this decision sequence:
- Assess airway, breathing, circulation, consciousness, urine output and trend in vital signs. A deteriorating trend matters even when one reading looks acceptable.
- Match support to location. High-flow oxygen and non-invasive ventilation may require ICU-level observation when the patient is unstable or tiring; invasive ventilation, vasopressors, acute dialysis or airway protection usually require an ICU.
- Reassess after treatment. Persistent low blood pressure, worsening oxygenation, confusion or failure of ward-level treatment calls for immediate escalation. Age or frailty alone should not exclude an ICU trial; discuss likely benefit and goals with the patient or surrogate.
Which treatments and test results trigger ICU specialist involvement?
ICU specialist involvement becomes necessary when a patient has actual or impending organ failure, needs life support, or requires continuous monitoring that a regular ward cannot safely provide. A chronic diagnosis alone is not the trigger; sudden deterioration is.
- Invasive mechanical ventilation is indicated when the patient cannot maintain oxygenation or carbon dioxide removal, protect the airway, or sustain breathing after noninvasive support. High-flow oxygen or noninvasive ventilation also warrants ICU observation when exhaustion or rapid deterioration is possible.
- Vasopressors and shock require critical-care review, especially when blood pressure remains low after fluids. In septic shock, vasopressors maintain a mean arterial pressure of at least 65 mm Hg, with lactate above 2 mmol/L after adequate fluids and without hypovolemia.
- Acute kidney injury and dialysis become urgent concerns with sharply falling urine output, severe potassium elevation, metabolic acidosis, pulmonary edema, or uraemic complications. A rising creatinine alone does not decide whether dialysis is needed.
- Suspected severe sepsis with a rising SOFA score signals worsening organ dysfunction. A SOFA increase of 2 or more supports sepsis-related organ dysfunction, but clinicians also assess blood pressure, oxygenation, mental status, urine output and treatment response.
| Trigger | What it indicates | Typical escalation |
|---|---|---|
| Respiratory failure | Oxygen or ventilation cannot be maintained | ICU and ventilatory support |
| Shock | Organs are under-perfused | Fluids, vasopressors and invasive monitoring |
| Kidney complications | Toxins, potassium or fluid are becoming dangerous | ICU monitoring and possible dialysis |
| Multiple organ dysfunction | Several systems are failing | Immediate critical-care assessment |
Who leads the decision: intensivist, emergency physician or another specialist?
The intensivist leads once deterioration requires ICU-level organ support or continuous critical-care monitoring. The emergency physician leads the first resuscitation, identifies immediately reversible threats and arranges admission or transfer. The practical distinction in intensivist versus emergency physician roles is timing: the emergency physician stabilises the crisis; the intensivist directs ongoing support.
| Role | Primary responsibility during deterioration | When that role leads |
|---|---|---|
| Emergency physician | Airway, breathing, circulation, urgent tests and initial treatment | In the emergency department or during the first acute collapse |
| Intensivist | Ventilation, vasopressors, invasive monitoring, organ support and ICU disposition | When failure is ongoing, worsening or involves several organs |
| Anaesthesiologist | Difficult airway management, intubation, sedation and selected procedures | When airway control or procedural expertise is the immediate danger |
| Pulmonologist | Lung diagnosis and treatment, including severe respiratory failure | When pulmonary disease drives the deterioration |
| Cardiologist | Acute coronary syndromes, arrhythmias and haemodynamic assessment | In myocardial infarction, unstable rhythm or cardiogenic shock |
| Primary treating physician | Medical history, baseline function, treatment goals and continuity | Throughout escalation, while coordinating with the acute-care team |
A pulmonologist and cardiologist may lead disease-specific treatment, but the intensivist coordinates competing organ-support decisions inside the ICU. For high-risk pulmonary embolism with persistent hypotension, right-ventricular failure or cardiac arrest, emergency and ICU teams involve cardiology, pulmonology or an embolism-response service for thrombolysis or embolectomy decisions.
No single specialist owns every decision. The lead changes as the patient moves from immediate resuscitation to definitive treatment and recovery.
What should families do before transfer and during the first ICU assessment?
If severe breathlessness, blue or gray lips, new confusion, fainting or inability to stay awake occurs, call emergency services. Do not drive the patient or send them to a rehabilitation appointment. Keep the patient upright unless unconscious, unlock the entrance, and give responders the address, symptoms, onset time and recent readings.
- Prepare the medication list and allergies, including dose, timing and the last dose taken.
- Pack discharge summaries, investigation reports, inhalers, insulin and identification.
- Tell the team about advance directives, resuscitation preferences and the person authorised to make decisions.
- If transfer follows a session at HealNext Clinic Baner, Pune, ask staff to include symptoms, vital signs and interventions in the handover.
The ICU team performs an airway breathing circulation neurological assessment before selecting oxygen, medicines or organ support. They check whether the airway is open and protected, how hard the patient is breathing, oxygen and carbon-dioxide levels, blood pressure, pulse, skin perfusion, urine output, consciousness, pupils and new weakness.
| Assessment | What clinicians check | Treatment decision it informs |
|---|---|---|
| Airway and breathing | Secretions, speech, work of breathing, oxygen saturation, blood gas and chest findings | Oxygen, high-flow oxygen, non-invasive ventilation or intubation |
| Circulation | Blood pressure trend, ECG, rhythm, capillary refill, lactate and urine output | Fluids, vasopressors, anti-arrhythmic treatment or cardiac support |
| Neurological status | Alertness, confusion, seizures and ability to protect the airway | Airway protection, imaging, sedation or urgent neurological treatment |
Related service
Critical Care Management – Expert Intensive Care Critical Care Management – Expert Intensive Care in Baner, Pune Critical care involves continuous monitoring and treatment of patients suffering from severe infections, respiratory failure, shock, multi-organ... View service → |
Frequently asked questions
Which warning signs mean a critically ill patient needs emergency assessment now?
Seek emergency assessment for severe breathing difficulty, blue or grey lips, shock signs, new confusion or unresponsiveness, seizures, uncontrolled bleeding, or rapidly worsening organ function.
What separates ICU care from ward, observation, or home monitoring?
An ICU provides continuous bedside monitoring, one-to-one or high-ratio nursing, rapid intervention, and organ support such as mechanical ventilation, vasopressors, or dialysis.
Which treatments and test results trigger ICU specialist involvement?
Escalating oxygen needs, non-invasive or invasive ventilation, vasopressors, severe sepsis, dangerous blood-gas results, persistent low blood pressure, severe arrhythmias, or acute kidney failure warrant specialist review.
Who leads the decision to admit a patient to intensive care?
The emergency physician stabilises and assesses the patient, while the intensivist decides whether ICU admission and organ support are needed with input from the relevant specialist.
What should families do before transfer and during the first ICU assessment?
Bring medication lists, allergies, diagnoses, records, and advance-care documents; provide a clear timeline and identify the legal decision-maker. Ask about the immediate threat, proposed support, and review plan.